IMPACT

ARCHES (Addressing Reproductive Coercion in Health Settings) has now been evaluated in multiple global contexts and health settings through rigorous controlled trials. In low- and middle-income country (LIMC) contexts, ARCHES was first adapted and evaluated in Nairobi, Kenya in a non-randomized cluster-controlled trial with women seeking family planning services. Since then, ARCHES has also been evaluated in cluster randomized controlled trials in Bangladesh with abortion clients and in Uasin Gishu, Kenya with family planning clients. The table below shows trials with results on ARCHES impact.  

Note: In Nigeria, Jhpiego has also completed a trial on ARCHES with family planning and antenatal care clients whose results are forthcoming.

Across adaptations and evaluations, four central themes have emerged about ARCHES impact. 

Impact on Reproductive Agency

Evidence from global adaptations of ARCHES supports that this simple, low-resource approach is effective in increasing women’s agency to:

  • Recognize and increase confidence that they CAN use contraceptive methods regardless of opposition from partners or family.
  • ACT on their decisions to use family planning to prevent pregnancy (including discreet family planning use).
  • RESIST reproductive coercion (RC) regarding their family planning and pregnancy decisions.

Among Women Seeking Family Planning Care:

  • ARCHES increases women’s self-efficacy (i.e., confidence) to use family planning methods in the face of opposition from male partners, including self-efficacy to use family planning discreetly compared to controls.
  • ARCHES increases family planning method uptake and use overall by 5-13% vs. controls.
  • ARCHES reduces incident pregnancy by 44%-126% vs. controls.
I used to follow what my husband and mother-in-law wanted blindly…I used to abide to their wishes to give birth. When she [the provider] made me aware that there were family planning methods that I can use without someone knowing really helped me…like the three months injectable that I could use without anyone noticing. I think that they [providers] should continue giving information to all the other women.​
Uasin Gishu, Kenya​
ARCHES Client

Impact on Violence Experiences

Evidence from global adaptations provides support that ARCHES, delivered by existing providers with minimal added time, is effective in increasing women’s agency to: ​

  • Recognize that they CAN access support services for their experiences of violence. ​
  • ACT to seek support for violence, if they choose. ​
  • RESIST and reduce intimate partner violence that they are experiencing in their relationships.​

Among Women Seeking Family Planning Care:

  • ARCHES increases women’s awareness of IPV support services by 11-193% compared to controls. 
  • ARCHES reduces subsequent experiences of IPV by 21-69% compared to controls. 
“If he [my husband] tells me something now, (laughs) I’ll show him the number [in the mini-booklet] and say, ‘I’ll call to these numbers and say that you are abusing me.’ Then he says, (laughs) ’I won’t say anything anymore’.”​
Bangladesh
ARCHES Client

Impact on Family Planning Quality of Care

Evidence from global adaptations of ARCHES supports that training existing family planning providers on the ARCHES elements increases the person-centered quality of care that women-receive and increases providers self-efficacy and ability to offer high-quality family planning care.

Providing such high-quality care leads to greater trust and sense of safety among women, increasing the likelihood that they will choose to disclose experiences of RC and IPV in this setting.

Among Women Seeking Family Planning Care:

  • ARCHES improves person-centered quality of family planning counseling by 37% and increases private counseling by 51% compared to controls.
  • ARCHES leads to high rates of disclosure of RC and IPV to providers (>50%) and improves detection of RC and IPV cases by 64-199% compared to controls.
  • ARCHES increases provider self-efficacy to provide high quality, person-centered care by 15-26% from pre to post training, an effect which was sustained at 6-month follow-up in Uasin Gishu, Kenya.
It has boosted my confidence. I used to think that family planning should be discussed by the couple, and they settle for one method of family planning. But in this case after training, I realized that it doesn’t necessarily have to be both of them and the person with the greater percentage of choice of the method lies with the person taking the method. So, for me the training has affected me positively and has even boosted my confidence in offering the services. Sometimes back when we were in school, they used to tell us that “you are not supposed to offer family planning services without consent from both partners”. But now with this, it’s the right of the person who is taking the method.​
Nairobi, Kenya​
ARCHES trained provider

Feasibility, Acceptability, and Fidelity

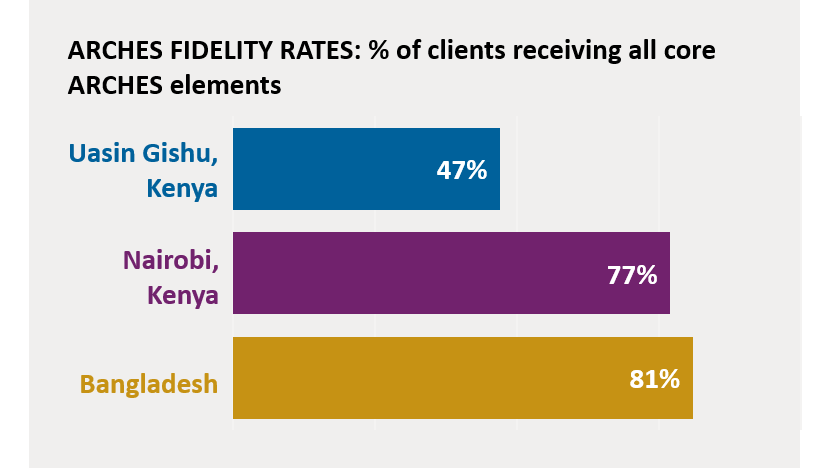
Across adaptations, providers have implemented ARCHES with high fidelity and found the model generally feasible and acceptable to implement.

In Uasin Gishu, Kenya, ARCHES was adapted for scale with a mobile app and while standard implementation rates were lower, the app was found to positively and substantially increase implementation of the intervention.

“There is no other platform to get this information from....with ARCHES, while counseling on family planning, one can come with reproductive coercion and IPV and they will get information on the same. I think ARCHES is handling this better.” ​
Nairobi, Kenya​
ARCHES trained provider