ARCHES (Addressing Reproductive Coercion in Health Settings) has now been evaluated in multiple global contexts and health settings through rigorous controlled trials. In low- and middle-income country (LIMC) contexts, ARCHES was first adapted and evaluated in Nairobi, Kenya in a non-randomized cluster-controlled trial with women seeking family planning services. Since then, ARCHES has also been evaluated in cluster randomized controlled trials in Bangladesh with abortion clients and in Uasin Gishu, Kenya with family planning clients. The table below shows trials with results on ARCHES impact.
Note: In Nigeria, Jhpiego has also completed a trial on ARCHES with family planning and antenatal care clients whose results are forthcoming.
Across adaptations and evaluations, four central themes have emerged about ARCHES impact.
Evidence from global adaptations of ARCHES supports that this simple, low-resource approach is effective in increasing women’s agency to:
Evidence from global adaptations provides support that ARCHES, delivered by existing providers with minimal added time, is effective in increasing women’s agency to:
Evidence from global adaptations of ARCHES supports that training existing family planning providers on the ARCHES elements increases the person-centered quality of care that women-receive and increases providers self-efficacy and ability to offer high-quality family planning care.
Providing such high-quality care leads to greater trust and sense of safety among women, increasing the likelihood that they will choose to disclose experiences of RC and IPV in this setting.
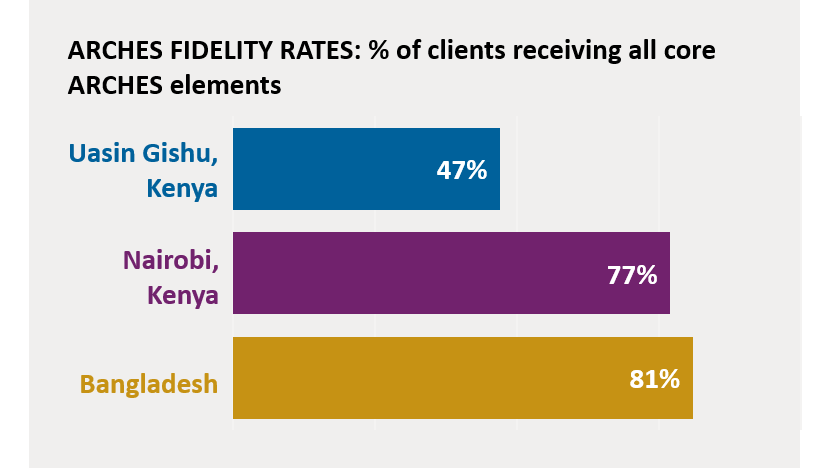
Across adaptations, providers have implemented ARCHES with high fidelity and found the model generally feasible and acceptable to implement.
In Uasin Gishu, Kenya, ARCHES was adapted for scale with a mobile app and while standard implementation rates were lower, the app was found to positively and substantially increase implementation of the intervention.